"This is my own essay for a university assignment (unpublished), not plagiarism. I’m sharing it as a way of practising my English."
Coma and Disorders of Consciousness: Clinical and Neuroscientific Insights, and the Default Mode Network as a Transdiagnostic Marker of Altered Consciousness
- BeeBlack translated by BeeBlack
Abstract
Disorders of consciousness following severe brain injury remain among the most challenging conditions to diagnose in clinical neuroscience, with reported misdiagnosis rates of 30 to 40% (Sanz, Laureys, & Gosseries, 2018). This article synthesizes a neuropsychopathology seminar on coma and disorders of consciousness before examining, in greater depth, how the default mode network (DMN) is altered across a range of neurological and psychiatric conditions and how this alteration can be modulated by therapeutic interventions. The first part outlines the conceptual distinction between arousal and awareness, the clinical spectrum from coma to locked-in syndrome, and the behavioral tools used to detect residual consciousness. The second part reviews DMN architecture, the factors that modulate its connectivity, its disruption in conditions such as Alzheimer's disease, depression, anxiety, autism, ADHD, PTSD, and schizophrenia, and the interventions, mindfulness, cognitive-behavioral therapy, cognitive remediation, transcranial magnetic stimulation, and neurofeedback, that appear to renormalize it. This article concludes that consciousness should be understood as the dynamic expression of distributed brain networks, and that DMN connectivity may constitute a promising transdiagnostic biomarker.
“If you have any questions about this topic, please send me an email. To make it more digestible, I’m adding small personal comments in blue. I tried to translate the terms I use as a French speaker as accurately as possible. In the U.S., the term ‘vegetative state’ is used for unresponsive wakefulness, whereas here we do not consider it to reflect an absence of brain activity.”
- BeeBlack
Introduction: The Diagnostic Challenge
Distinguishing patients in an unresponsive wakefulness syndrome (UWS) from those in a minimally conscious state (MCS) is one of the most consequential tasks in clinical neuroscience, and one of the most error-prone: diagnostic errors are estimated at 30-40% (Sanz, Laureys, & Gosseries, 2018; Gosseries, 2026). Detecting the presence or absence of consciousness is critical because the absence of language does not equal the absence of consciousness, a distinction that carries direct consequences for prognosis and therapeutic decision-making. These diagnostic stakes are inseparable from ethical ones, since decisions about continuing or withdrawing care hinge on this assessment. Together, these considerations justify the need for a rigorous, multimodal diagnostic approach that combines repeated behavioral examination with neuroimaging and electrophysiological tools.
“Relying solely on the Glasgow Coma Scale is inadequate, and clinical errors tend to rise."
Part 1. Seminar : Coma and Disorders of Consciousness
Defining Consciousness: Arousal and Awareness
Consciousness is classically decomposed into two components (Gosseries, 2026).
Arousal (Wakefulness) corresponds to eye opening, vigilance, and cortical activation, and is supported subcortically by the brainstem, thalamus, and striatum, together forming the mesocircuit.
Awareness (Conscious perception), or subjective experience, corresponds to the internal and external lived perception of the world and of oneself. Its internal component is thought to rely on the default mode network, whereas its external component recruits fronto-parietal networks. This distinction, between being awake and being aware, underlies the entire clinical spectrum of disorders of consciousness, since arousal and awareness can be dissociated after severe brain injury.
"The main idea is that consciousness has two parts: one for the body and one for the mind. For the mind, there’s internal perception (daydreaming, thinking) and external perception (paying attention to what’s around you)."
Mapping the States of Consciousness
Beyond pathological states, physiological and altered states illustrate how arousal and awareness can vary independently or together. Conscious wakefulness combines arousal with full subjective experience. Slow-wave sleep is characterized by a marked decrease in subjective experience, whereas REM sleep is associated with a rich internal experience, namely dreaming. Lucid dreaming adds a further layer of metacognition, or awareness of the dream state itself. Finally, altered states such as hypnosis, trance, and psychedelic states illustrate additional configurations of arousal and awareness (Sanz, Laureys, & Gosseries, 2018; Gosseries, 2026) (cf. Fig 1).
"Internal conscious perception is active during lucid dreaming, while wakefulness is not. Lucid dreaming enables voluntary influence over the dream. Coma must be differentiated from brain death, as recovery is possible from coma but not from brain death."
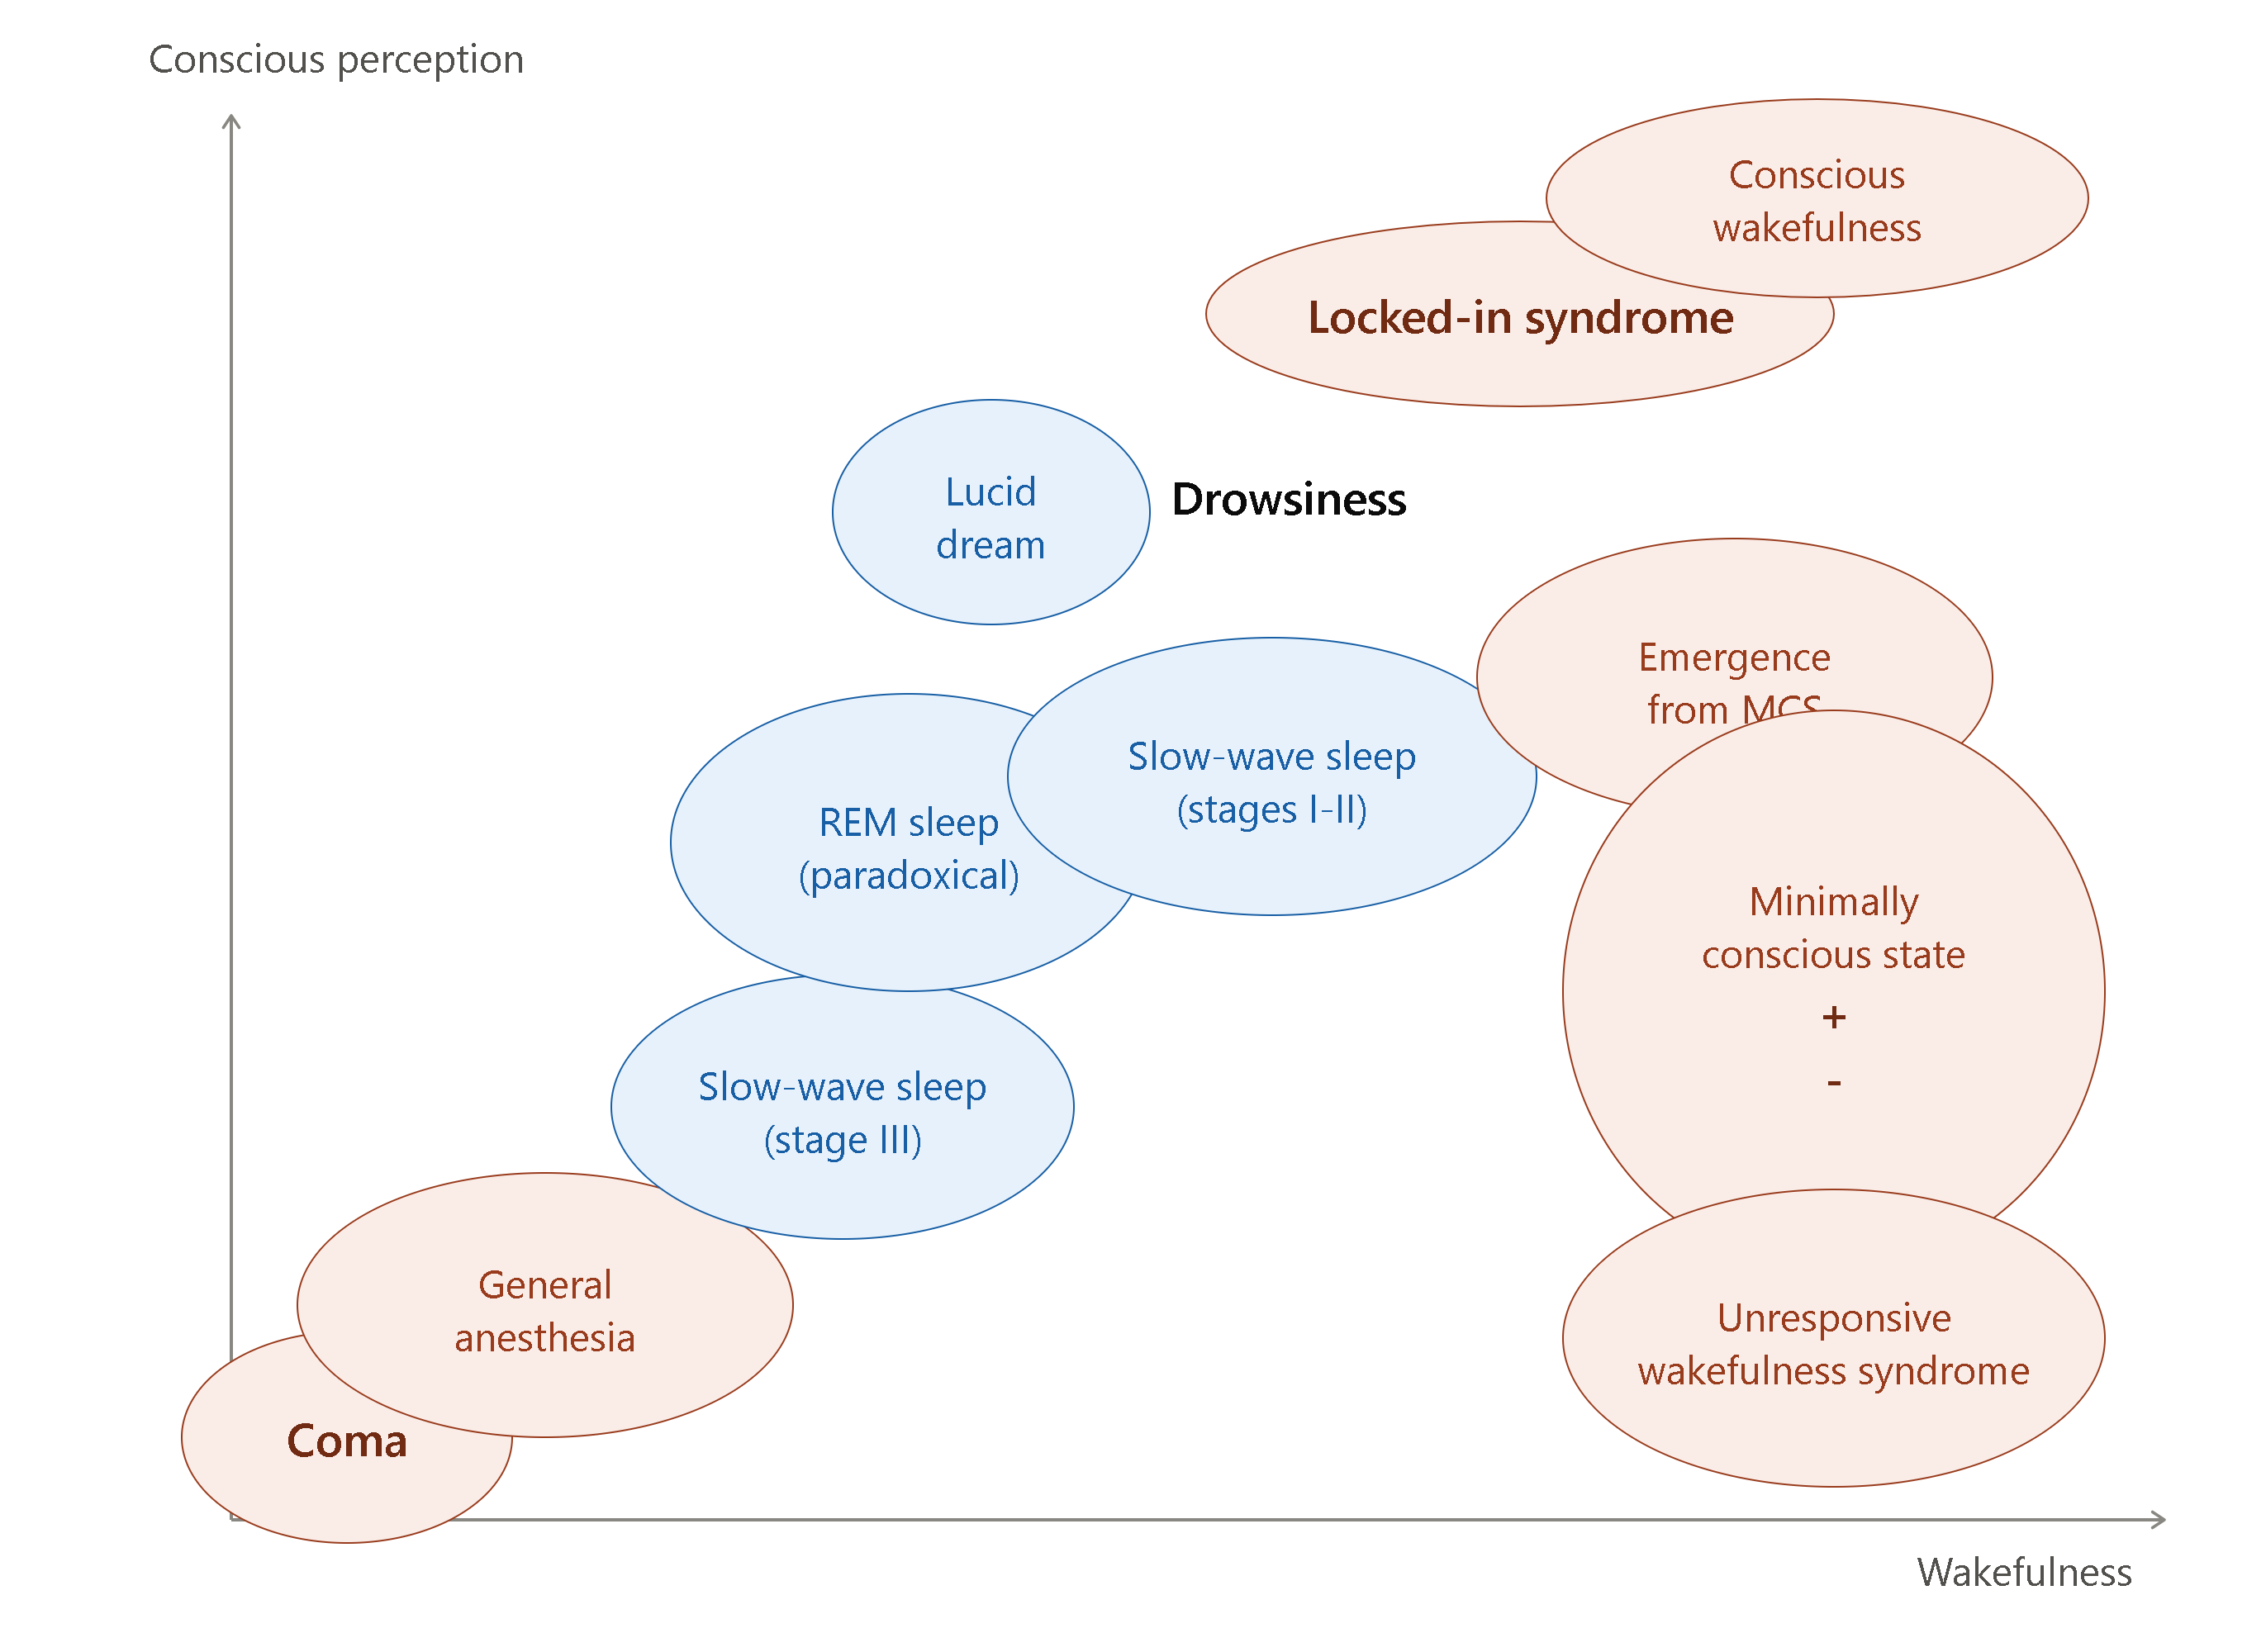
Fig 1. Map roughly translated from Sanz, Laureys, & Gosseries, (2018)
Clinical Assessment of Disorders of Consciousness
Clinically, patients recovering from coma are assessed across six functional domains (auditory, visual, motor, oromotor, communicative, and arousal) that together distinguish the unresponsive wakefulness syndrome (UWS), the minus and plus variants of the minimally conscious state (MCS- and MCS+), emergence from MCS, locked-in syndrome, and coma (Gosseries, 2026). A patient in locked-in syndrome, for instance, may show a systematic response to command and object recognition despite an absence of spontaneous motor output, whereas the profile of cognitive-motor dissociation (CMD) is behaviorally indistinguishable from UWS at the bedside, yet conceals residual consciousness detectable only through ancillary techniques.[1]
"People don't remain in a coma for decades (without regaining consciousness or wakefulness). They progress from a comatose state to a state of unresponsive wakefulness)"
The Coma Recovery Scale-Revised (CRS-R)
The CRS-R is the reference behavioral scale for this assessment, evaluating auditory, visual, motor, oromotor, and communicative function as well as arousal level through 23 items distributed across six subscales (Gosseries, 2026). Three signs are considered major markers of consciousness: response to command, visual fixation and pursuit, and localization to pain. A single occurrence of one of these signs is sufficient to establish a diagnosis of MCS, provided it is observed reproducibly across the four trials of the scale. Additional, supplementary signs of consciousness include crossing the legs, eye blinking, olfactory reaction, and swallowing.[2]
"This scale is widely used in Europe. In the United States, they still use the Glasgow scale, which further increases the likelihood of misdiagnosis."
The Contribution of Neuroimaging and EEG
Because behavioral scales alone cannot reliably detect covert consciousness, several complementary tools are used alongside the CRS-R: positron emission tomography (PET), structural MRI (sMRI), functional MRI (fMRI), electroencephalography (EEG), and transcranial magnetic stimulation (TMS) (Gosseries, 2026). These techniques make it possible to identify residual cortical activity or command-following in patients who show no behavioral evidence of consciousness, and are central to detecting cognitive-motor dissociation.
"For information, functional imaging uses AI to refine the identification of cognitive impairment. However, clinical verification remains necessary."
Part 2. In-Depth Focus: Default Mode Network Alteration Across Pathologies and Modulating Tools
The Default Mode Network (DMN)
The default mode network comprises three interconnected functional subsystems: a central hub, a medial temporal subsystem, and a medial prefrontal subsystem. It is characteristically inhibited upon activation of the salience network and the fronto-parietal network, reflecting a broader dynamic of anticorrelation between task-negative and task-positive networks (Fox et al., 2005). Far from being a mere resting-state artifact, the DMN is dynamic and adaptive, supporting self-construction, autobiographical episodic memory, projection into the past and future, theory of mind, and creativity and imagination (Andrews-Hanna, Smallwood, & Spreng, 2014; Bastin, 2018; Beaty et al., 2018; Buckner, Andrews-Hanna, & Schacter, 2008; Leech & Sharp, 2014; Raichle, 2015; Spreng & Grady, 2010; Smith, Mitchell, & Duncan, 2019; Soares, Gonzalo, Castelhano, & Castelo-Branco, 2023; Yeshurun, Nguyen, & Hasson, 2021).
"Indirectly, other processes are also involved. However, when we refer to the default mode network, we are specifically referring to the connections between the precuneus, the posterior cingulate gyrus, the ventral and dorsal frontomedial cortex, the inferior parietal lobule, and, in some cases, the medial temporal gyrus, depending on the experimental context."
Factors Modulating the DMN
DMN connectivity is not fixed: it is modulated by altered states of consciousness (Ho et al., 2015; Sampaio et al., 2014), by emotions and personality (Bauer et al., 2019; Bremer et al., 2022; Brewer et al., 2011; Soares et al., 2023), by age (Malagurski, Deschwanden, Jäncke, & Mérillat, 2022), and by environmental factors, including early-life adversity (Hanson et al., 2015; McLaughlin, Sheridan, & Lambert, 2014). This modulability is precisely what makes the DMN a plausible substrate for both vulnerability and therapeutic change.
"The main modulatory neurotransmitters are glutamate, noradrenaline, and acetylcholine. The others are directly involved in the default mode network to varying degrees, ensuring its proper functioning."
Disorders: DMN Dysconnectivity Profiles
Across a wide range of neurological and psychiatric conditions, the DMN shows distinct, partly overlapping dysconnectivity profiles.
"This is a corpus of recent research examining alterations of the default mode network in various pathologies. The key takeaway is that this network plays a more critical role than commonly assumed, and despite methodological limitations that hinder consensus, its disruptions consistently show significant effects."
|
Disorder |
DMN alteration |
Correlates |
|
Alzheimer's disease / aMCI |
Decreased intra-DMN connectivity, decreased metabolism, and abnormal coupling with other brain networks (Wang et al., 2026; Wu et al., 2023; Zhang et al., 2024). |
Memory deficits. |
|
Depression |
Altered mPFC–PCC/precuneus intra-DMN connectivity and increased coupling with limbic regions (Chou, Deckersbach, Dougherty, & Hooley, 2023; Greicius et al., 2007; Ho et al., 2015; Javaheripour et al., 2023; Sheline, Price, Yan, & Mintun, 2010; Tozzi et al., 2021). |
Rumination and symptom severity. |
|
Anxiety |
Decreased intra-DMN connectivity and disrupted inter-network connectivity (Cunha, Vandenbusche, Karayel, Vivet, & Kadri, 2025). |
Reduced inner speech and increased threat-related hyperactivity / task-focused attention. |
|
Autism |
Increased intra-DMN connectivity together with decreased connectivity between the DMN, the salience network, and the fronto-parietal network; profiles are heterogeneous (Uddin et al., 2015). |
Repetitive and restricted behaviors. |
|
ADHD |
Decreased intra-DMN connectivity and interference between the DMN and attentional networks; profiles are heterogeneous (Fateh et al., 2023; Wong, Zhang, White, Xu, & Qiu, 2021). |
Distractibility and irritability. |
|
PTSD |
Disrupted mPFC–PCC coupling within the DMN and altered PCC/precuneus–hippocampus coupling; profiles are heterogeneous (Averill et al., 2024; Chaposhloo et al., 2023; Etkin & Wager, 2007). |
Re-experiencing, stress, and avoidance. |
|
Schizophrenia |
Altered intra-DMN connectivity and dysfunctional coupling between the DMN and other networks; profiles are heterogeneous (Li et al., 2019; Menon, 2020; Mehta et al., 2021; Okano et al., 2020). |
Hallucinations, cognitive deficits, and disorganization. |
Note. Intra-DMN connectivity refers to the internal coherence of the network; inter-network connectivity describes its relation to other systems; coupling refers to synchronization/desynchronization dynamics between networks; and metabolism reflects the energetic cost of the underlying neural activity.[3]
Intervention Approaches Related to the DMN
Several therapeutic and neuromodulatory approaches appear capable of renormalizing DMN connectivity.
“The key point is that the clinical and experimental interventions described below exert their effects on the default mode network.”
|
Approach |
Observed effects |
|
Mindfulness |
Decreased DMN activity, appearing to improve attentional and emotional regulation (Bauer et al., 2019; Bremer et al., 2022; Zhang et al., 2023). |
|
Cognitive-behavioral therapy (CBT) |
Normalizes DMN connectivity in anxiety and depressive disorders through behavioral activation (Goldin et al., 2014; Teng, Liu, Zhang, Zhong, & Wang, 2022; Yokoyama et al., 2018). |
|
Cognitive remediation |
Increases intra-DMN coupling in mild cognitive impairment (MCI), improving global cognitive function through computerized cognitive training (Wu et al., 2023). |
|
Transcranial magnetic stimulation (TMS) |
Rebalances interactions between the DMN and attentional or emotional networks (Davidson et al., 2024; Marques, Vieira, Marques, & Cantilino, 2019). |
|
fMRI- or EEG-based neurofeedback |
Normalizes resting-state connectivity in people with schizophrenia, with a potential reduction in auditory hallucinations, and normalizes intra-/inter-hemispheric networks in post-stroke patients, with a potential reduction in motor symptoms (Bauer et al., 2020; Davidson et al., 2024; Lamouroux, 2025; Okano et al., 2020; Zhang et al., 2023). |
Note. aMCI = amnestic mild cognitive impairment; MCI = mild cognitive impairment.[4]
Limitations and Perspectives
This body of research faces several limitations, including small sample sizes and substantial inter-individual variability, marked methodological heterogeneity across studies, and the persistent risk of conflating correlation with causation. In the specific case of neurofeedback, the standardization of data pipelines remains an open challenge (Lamouroux, 2025). Several perspectives emerge in response: standardizing analysis pipelines, illustrated by the fMRIStroke pipeline developed for post-stroke populations, fusing EEG with functional imaging, adopting longitudinal approaches to track DMN evolution over time, designing network-targeted interventions, and, ultimately, working toward transdiagnostic biomarkers of altered connectivity (Lamouroux, 2025).
“Neurofeedback remains a non‑consensual field, yet the studies presented here are generally methodologically sound. These are not pseudoscientific claims from charlatans selling overpriced devices. No quantum mysticism or other scientific fallacies.”
Conclusion
Taken together, these two strands of work converge on a unifying view of consciousness: it is best understood as the dynamic expression of brain networks within the central nervous system, such that the same clinical behavior can correspond to different underlying brain states. Alterations of these networks, and of the default mode network in particular, may constitute a potential transdiagnostic marker across neurological and psychiatric conditions, opening the way to new theoretical hypotheses. Clinically, this perspective offers concrete avenues to improve diagnosis, refine prognosis, and develop care approaches tailored to each patient's underlying brain state rather than to behavior alone.
“I attempted to make the topic accessible without oversimplifying it, but the default mode network cannot be meaningfully reduced beyond a certain point. The terminology used reflects my own translation of European concepts, so minor imprecisions may remain.”
Reference
"If you’re interested, please email me"
[1]Two behaviorally indistinguishable but conceptually distinct entities may underlie an apparently identical clinical presentation: the unresponsive wakefulness syndrome (UWS) and cognitive-motor dissociation (CMD), in which residual covert consciousness is detectable only through neuroimaging or electrophysiology, not at the bedside (Gosseries, 2026).
[2]The Coma Recovery Scale-Revised (CRS-R) remains the reference behavioral scale in this field, but diagnostic error rates of 30-40% persist when it is used in isolation, underscoring the need for multimodal assessment combining behavioral and neuroimaging/electrophysiological markers (Sanz, Laureys, & Gosseries, 2018; Gosseries, 2026).
[3]Intra-network connectivity refers to the internal coherence of a given network (e.g., the DMN); inter-network connectivity describes its relationship with other large-scale brain systems; coupling refers to the dynamic synchronization or desynchronization between networks; and metabolism reflects the energetic cost of the underlying neural activity.
[4]aMCI = amnestic mild cognitive impairment; TCC = cognitive-behavioral therapy; MCI = mild cognitive impairment.